

Most take their first cognitive test after they or a family member notice a problem. Their results are then interpreted in a vacuum. There is no record of their performance from when they were well, so it is difficult to assess what has changed, by how much, and how quickly.
Cancer and heart disease are screened for years before symptoms appear, and as highlighted in a recent Medical Economics article, cognitive health warrants a similar approach. The brain changes behind mild cognitive impairment (MCI), Alzheimer’s disease, and other dementias can build for 10 to 20 years before their first symptoms. Catching them earlier can expand the window to address risk factors and plan care.
Radence addresses the cognitive testing gap by measuring how members function while they are well. That record becomes a personalized baseline used to flag and address change in the years that follow.

Where Conventional Screening Falls Short
Brief screens such as the Montreal Cognitive Assessment (MoCA) take 10 to 15 minutes and sample memory, attention, language, executive function, visuospatial skills, abstract reasoning, and orientation. They can identify moderate to severe impairment but are much less sensitive to early decline, and their scores are judged against population averages rather than an individual’s history.
This is a problem for people who have always functioned at a high cognitive level, those often with advanced education or demanding careers. These individuals typically have a high cognitive reserve which allows the brain to compensate as performance slides due to undetected changes. Someone whose memory and processing speed were once exceptional can decline substantially and still score in the normal range. A personal baseline lets clinicians compare new results with their earlier performance as well as with population norms.
What Comprehensive Testing Adds
A comprehensive neuropsychological assessment, administered by a neuropsychologist over 3 to 5+ hours, evaluates cognitive abilities at significantly greater depth. It uses a set of standardized tests to assess each cognitive domain, including memory, attention, executive function, language, visuospatial skills, and processing speed.
The data gathered across these domains helps point to a cause. Trouble forming new memories is typical of Alzheimer’s disease, slowed processing and difficulty with multistep tasks suggest vascular changes, and changes in planning or behavior with memory intact can indicate frontotemporal dementia. Inconsistent recall can instead reflect medications, attention disorders, sleep apnea, or fatigue. A MoCA screen cannot distinguish among these.
Radence administers the MoCA to every member and repeats it at a regular cadence. Any member can choose to have comprehensive testing to establish a detailed baseline, and Radence recommends it on an individualized basis, especially if:
- A member receives a screening score much lower than expected
- A family history of dementia
- Changes in memory, focus, or behavior noticed by the member or their family
- An APOE4, PSEN1, or PSEN2 (or other clinically pertinent neurodegeneration genes) result on genetic testing
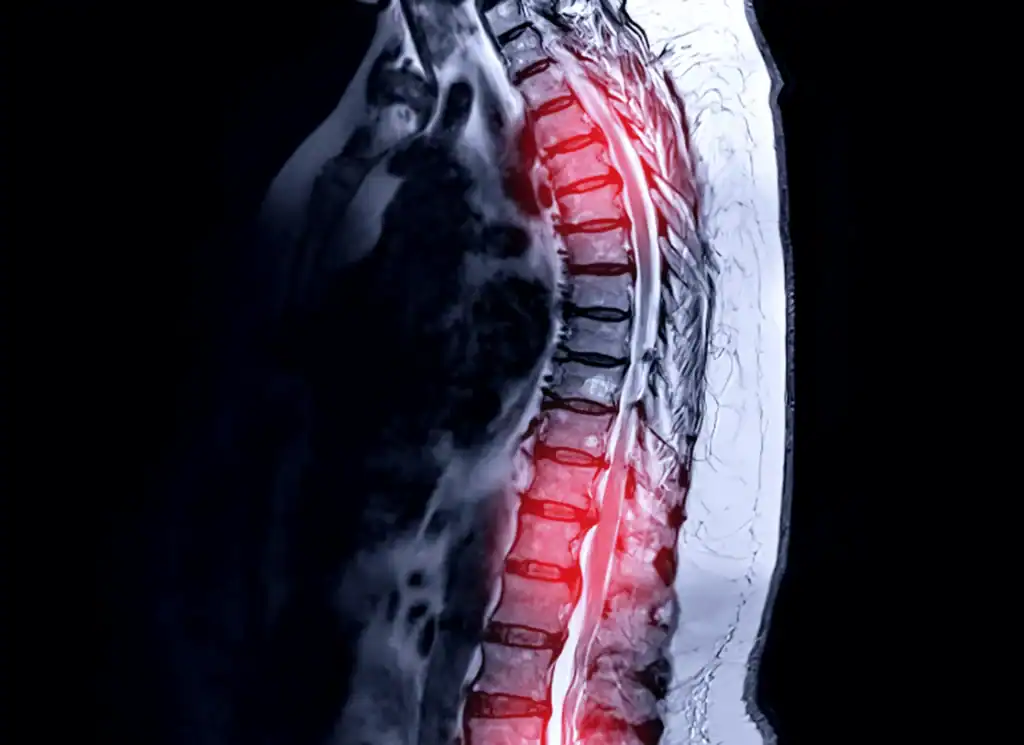
- White matter changes or other relevant findings on brain imaging
The Radence Testing Framework
Standardized sets of neuropsychological tests exist, but they are not widely used in clinical practice. Most neuropsychologists use their own flexible set of tests, which varies within and across institutions; however, this makes results from one practice potentially difficult to compare with results from another. For a patient who relocates, seeks a second opinion, or sees a new specialist, that could mean a time-consuming retest.
To address this, Radence evaluated more than 95 neuropsychological tests with practicing clinicians at world-leading academic and community institutions. We then refined that test set to those used most routinely by the institutions surveyed. An evidence-informed framework for comprehensive cognitive assessment was then developed using well-established tests selected for broad domain coverage, portability, and practical duration. Almost every test included is sensitive to MCI, the early stage of decline that precedes dementia. Every consulted neuropsychologist stated they would accept results from the framework without retesting, provided it was administered by a credentialed clinician with complete documentation.
When comprehensive testing is warranted, Radence coordinates it with an independent neuropsychologist who is free to adjust it based on their clinical judgment. Because the framework uses widely accepted tests, a member’s results remain interpretable by other institutions and specialists. After a baseline is established, Radence retests at an interval set for each member to gather longitudinal trends and track any new symptoms.

Putting Cognitive Results in Context
Radence reviews cognitive results alongside other measures of brain health. Blood biomarkers such as p-tau217 can detect early Alzheimer’s-related changes from a standard blood draw, and APOE, PSEN1, PSEN2, etc. genotyping identifies genetic risk. Brain MRI through the BioAtlas protocol shows white matter changes, and referral to neurodegeneration specialist to discuss external amyloid PET imaging if findings warrant it. Cardiovascular, metabolic, and family history are considered as well. Slowed processing speed on testing, white matter changes on MRI, and elevated cardiovascular risk, for example, together point to a vascular contribution that can be addressed. Vascular damage and Alzheimer’s-related changes also often occur together, and when they do, symptoms can appear with less Alzheimer’s-related change than would otherwise be expected.

After the Assessment
Neurodegenerative diseases, like Alzheimer’s, can begin in the brain decades before symptoms appear, and cutting-edge treatment timing is crucial to the efficacy and safety of therapy. Recognizing change early, against a personal baseline, keeps more options available.
Radence interprets cognitive findings in the context of each member’s overall health, decides on next steps, and connects members with vetted specialists when further evaluation or treatment is needed. Radence clinicians can join those appointments to share findings with the care team, and they continue to track results over time.
A more complete picture of your health stars with understanding your baseline.
At Radence, cognitive assessment is part of a broader, ongoing understanding of each member’s health. We connect findings across cognitive testing, imaging, biomarkers, genetics, and other clinical information to determine what deserves attention and what should happen next. When specialist evaluation or treatment is needed, we help identify the right expertise, work alongside existing physicians, and stay involved as the picture evolves. We help you understand what is changing while there is still time to act on it.